
Structured CRitical Airway Management
The SCRAM™ Story
A team can carry everything it needs and still have too much to organise at the scene. SCRAM™ grew from examining how that preparation work could be designed differently.
Read the originWhy SCRAM™ exists
It began with a preparation problem.
SCRAM™ — Structured CRitical Airway Management — began with a practical question about emergency airway care: how much preparation could be organised before the team reached the patient?
A familiar approach is to create a kit dump, laying out the equipment needed for emergency anaesthesia and tracheal intubation on a clinical waste bag or preparation sheet. That gives the team a working structure, but it takes time to unpack, select and arrange the equipment while other clinical work is already under way.
The Association of Anaesthetists’ 2026 guidance continues to recommend a standardised kit dump, team training in equipment preparation and layout, and a pre-induction checklist. Those requirements make preparation part of the team’s shared work. They also leave a practical design question: how can the equipment support that work in the setting where it will be used? 1
I co-invented and developed SCRAM™ with Neil Sinclair to address that preparation problem.
In pre-hospital care, the layout also has to withstand wind, weather, limited space and movement. A team can know the procedure well and still have to spend attention keeping its preparation together. The design problem was in that additional work and the conditions in which it had to be done.
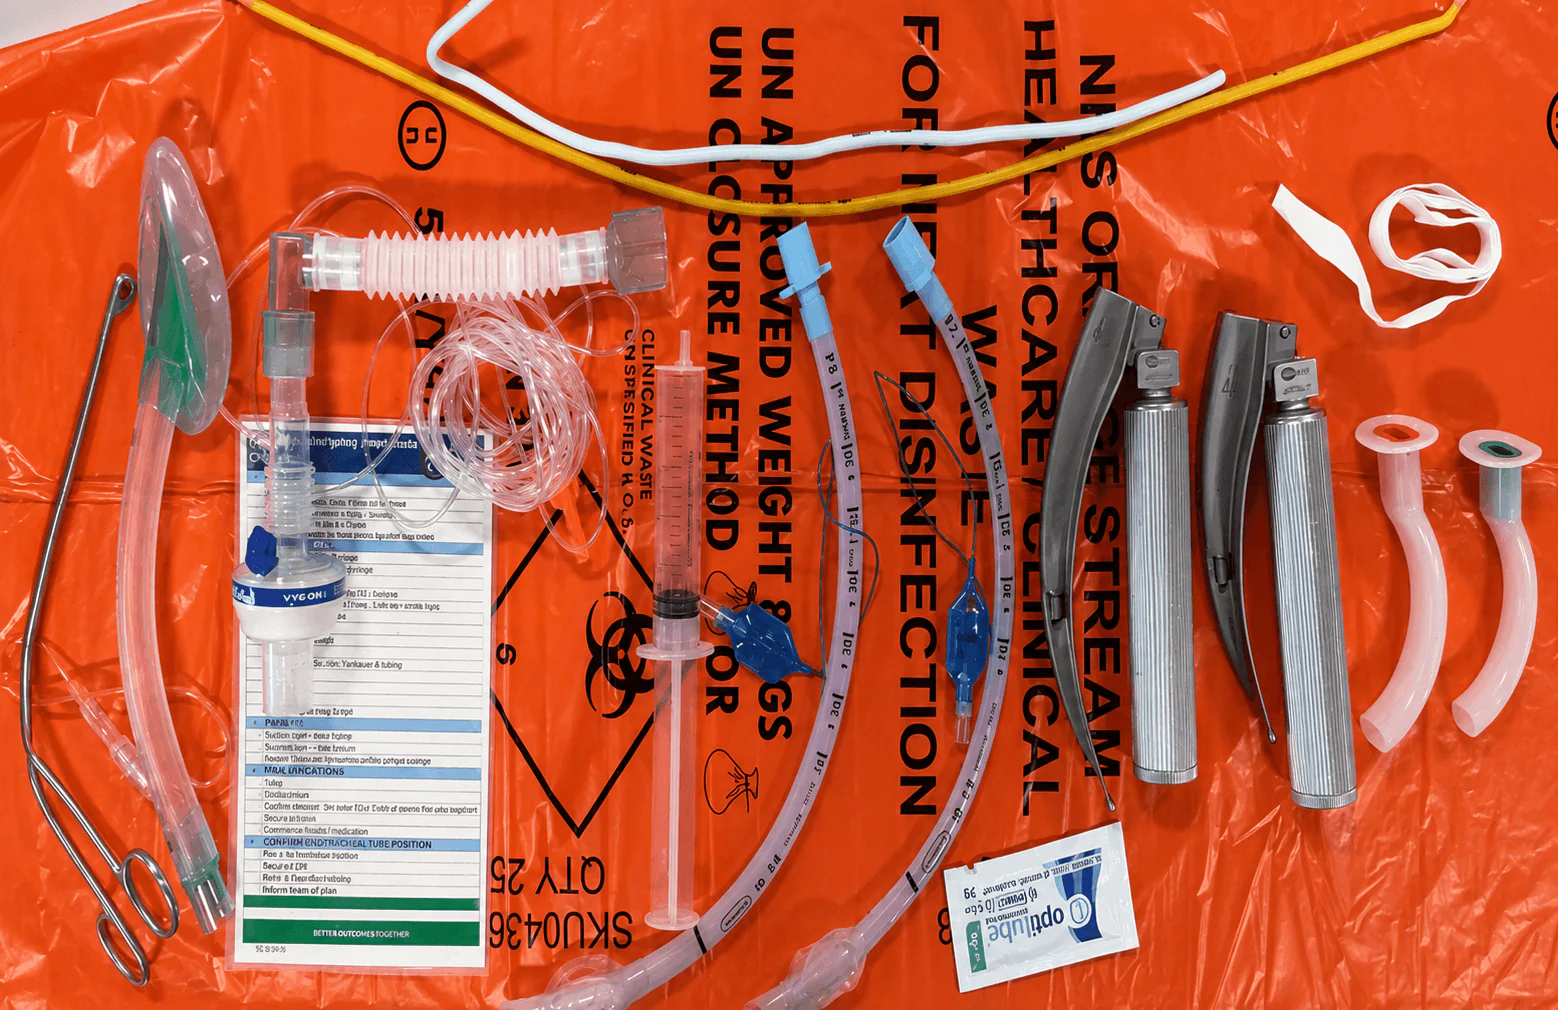
Equipment laid out on a clinical waste bag.
A recognised and familiar method for creating an airway kit dump at the scene.

Equipment arranged on a structured preparation sheet.
A preparation sheet provides a visible sequence and prompts for the team.
The work behind preparation
What the team still had to do.
Carrying all the equipment is only one requirement. The team also needs to find it, check it and make it ready for use.
Bring the required equipment into view.
Items stored for transport still have to be located and selected. The layout needs to support that work without requiring someone to remember where everything has been packed.
Make readiness easier to examine.
Equipment has to be organised around the intervention, with omissions and backup requirements considered before it is needed.
Keep the preparation usable.
Movement or a change of working position can disrupt a kit dump. Retaining items within the layout was therefore part of the design problem, alongside visibility and access.
The design question
Could preparation change the work?
The time, decisions and checking involved in getting ready.
Can preparation itself be designed to reduce procedural time, error rate and cognitive load?
NAP4’s review of major airway complications in intensive care and emergency departments identified problems with planning, equipment, staffing and recognising difficulty. 2 These findings show why airway preparation needs to extend beyond having the right equipment available. It also means considering how that equipment is organised, whether the team is ready to use it and what support is available if difficulties arise.
We broke emergency anaesthesia and tracheal intubation down into their component tasks. Preparation stood out because it accounted for work that could be organised earlier, while also shaping what happened during the procedure.
Durrand and colleagues discussed the aggregation of marginal gains in prehabilitation: considering several areas of preparation together rather than expecting one change to account for the whole improvement. 3 For SCRAM, the useful question was which changes would make a difference. Moving work earlier would only help if the equipment remained complete, accessible and ready when required. It also meant considering how the system would be checked and restored after use.
Process improvement through design
The gain is not the 1%. It is knowing which 1% changes the work.
Small changes need a clear purpose.
Not every change matters equally.
A consistent equipment position can remove a search. A visible layout can make an omission easier to notice. Preparing a task earlier can reduce the work left at the scene. These are specific changes to how preparation is done; their value has to be examined in use.
The studies below examined preparation time, errors and reported workload. They did not establish the contribution of each individual design feature.
2018 simulation findings
Procedural time
reducedErrors
reducedAssistant cognitive load
reducedIn an emergency airway, preparation is part of the procedure.
Evidence
Preparation changes performance.
The research examined what happened when preparation was organised differently: the time required, the errors made and the workload experienced by the team.
Pre-preparation changed the conditions of the procedure.
A randomised crossover simulation study examined pre-prepared equipment and drugs for pre-hospital emergency anaesthesia. Compared with standard practice, the experimental method reduced procedural time, reduced procedural errors and reduced the cognitive load experienced by the intubator assistant. 4
The important finding was not simply that the procedure became faster. The preparation system changed the work: less time spent setting up, fewer errors during preparation and delivery, and less cognitive burden placed on the assistant during the simulated procedure.
Design signal: Preparation is not background work. It is a fundamental part of clinical performance.
The SCRAM bag changed remote-site kit-dump performance.
In a simulated remote-site difficult-airway scenario, use of the SCRAM bag was associated with quicker kit-dump completion, fewer errors and lower perceived difficulty when compared with a standard resuscitation trolley. 5
Evidence signal: The preparation layout changed how the task was performed, including the omissions made and the difficulty experienced by the person preparing the equipment.
The design problem translated into paediatric systems.
Paediatric simulation work reported shorter kit-dump completion time, fewer errors and lower self-reported cognitive load. Published as a conference abstract, the study involved 12 participants using the paediatric SCRAM bag without prior training. 6
In 2023, Pope and colleagues described a paediatric airway quality-improvement project at the Royal Hospital for Children, Glasgow. Using Lean/Six Sigma methodology, they introduced SCRAM alongside changes to equipment provision and an emphasis on high-quality basic airway management by initial responders. The authors reported lower hospital costs and less waste of unused equipment, while identifying further staff training as essential. This brings the design question into everyday service delivery: how equipment is organised, who uses it and what preparation staff need to make the arrangement work. 7
SCRAM™ as the mechanism
The system has to do more of the work.
SCRAM™ was developed to improve the preparation and delivery of emergency anaesthesia and tracheal intubation by organising the work around the intervention.
In high-pressure clinical environments, even experienced clinicians can be short of time, space, certainty and spare cognitive bandwidth.
The more a clinician has to search, select, interpret and reorganise under pressure, the more avoidable cognitive load enters the system.
SCRAM™ organises equipment around the sequence of the intervention: a structured, reproducible kit dump that makes essential components visible, reduces unnecessary searching and reorganisation, and gives the team a shared reference point before the procedure begins.

Why SCRAM™ is different
A preparation system, not just a bag.
SCRAM™ is a structured, reproducible approach to airway management, standardising and organising equipment — and, where appropriate, drugs — before they are required.
A repeatable preparation system.
Preparation becomes less dependent on improvisation at the scene and more dependent on a clear system.
A shared layout.
Equipment is arranged to support a common mental model and quicker team orientation.
Less avoidable load.
The layout is designed to reduce unnecessary searching, reorganisation and decision burden.
Visible, checkable preparation.
Load lists and checklists make the system easier to inspect, maintain and improve.
Keeping that structure dependable requires clear responsibility for loading, checking and replenishment. Changes to equipment or layout also need to be managed, so the team can rely on what it expects to find.
Drug preparation
Equipment was only part of the story.
Drug preparation was part of the original research because organising equipment alone would leave a substantial part of the preparation task untouched.
Selecting, preparing and labelling drugs creates its own opportunities for error. Jensen and colleagues’ review examined ways to reduce drug-administration errors in anaesthesia, including the organisation and checking of that work. 8
Preparing earlier also brings decisions about storage, labelling, stability, waste and responsibility. Those need to be resolved through the service’s medicines governance. A layout can support the process, but it cannot establish that a particular preparation method is appropriate for every setting.

The SCRAM™ portfolio
Clinician feedback shaped the range.
Different clinical environments brought different requirements for equipment, space and portability. The SCRAM™ configurations developed around those needs while retaining a common approach to preparation.
Openhouse Products manufactures and distributes the system; The Resus Tailor is a distributor. The EMCrit collaboration applies to the specific configurations identified below.
The product pages explain the individual designs and provide routes for orders and enquiries. Shared principles do not mean every configuration has the same evidence base.
Research
Read the research behind SCRAM™
The research page brings together the publications, abstracts and related work on emergency airway preparation.
View research and publicationsPerformance by Design
Preparation is part of performance.
SCRAM™ began with a specific problem in emergency airway preparation. It is also an example of how I approach clinical design: examine what the team has to do, identify work that can be organised earlier, and test whether the change helps.
The wider question is how much work a clinical system leaves for people to resolve under pressure. Answering it means considering equipment alongside workflow, training and the responsibilities that keep the system dependable. That is why, for me, the design work continues after a product is made.
Explore my writing on clinical systemsReferences
- Lockey D, Weegenaar C, Ahmad I, Avery P, Cowburn P, Lyon RM, et al. Safer prehospital anaesthesia: updated guidelines from the Association of Anaesthetists. Anaesthesia. 2026;81:1132–1147. Read publication 1
- Cook TM, Woodall N, Harper J, Benger J; on behalf of the Fourth National Audit Project. Major complications of airway management in the UK: results of the Fourth National Audit Project of the Royal College of Anaesthetists and the Difficult Airway Society. Part 2: intensive care and emergency departments. British Journal of Anaesthesia. 2011;106:632–642. Read publication 2
- Durrand JW, Batterham AM, Danjoux GR. Pre-habilitation (i): aggregation of marginal gains. Anaesthesia. 2014;69:403–406. Editorial. Read publication 3
- Swinton P, Corfield AR, Moultrie C, Percival D, Proctor J, Sinclair N, Perkins ZB. Impact of drug and equipment preparation on pre-hospital emergency anaesthesia (PHEA) procedural time, error rate and cognitive load. Scandinavian Journal of Trauma, Resuscitation and Emergency Medicine. 2018;26:82. Read publication 4
- Schyma BM, Wood AE, Sothisrihari S, Swinton P. Optimising remote site airway management kit dump using the SCRAM bag—a randomised controlled trial. Perioperative Medicine. 2020;9:11. Read publication 5
- Wylie M, Waters E, McCormack J, Swinton P. The SCRAM bag: a comparison between current practice versus a novel standardized approach for in-hospital pediatric emergency airway management. Critical Care. 2021;25(Suppl 1):P140. Conference abstract. Read publication 6
- Pope J, Boyle J, Worrall M. Airway management in paediatric emergencies outside of an intensive care setting: a quality improvement project using Lean/Six Sigma methodology. Archives of Disease in Childhood — Education and Practice Edition. 2023;108:463–466. Read publication 7
- Jensen LS, Merry AF, Webster CS, Weller J, Larsson L. Evidence-based strategies for preventing drug administration errors during anaesthesia. Anaesthesia. 2004;59:493–504. Read publication 8